
Lead Malposition vs Dextrocardia: ECG Clues to Tell Them Apart
Case Presentation (H2) A 26-year-old female, normally healthy and on no medications except oral contraceptive pills, presented to the Emergency Department with: 1-day history of left-sided chest pain
Case Presentation
A 26-year-old female, normally healthy and on no medications except oral contraceptive pills, presented to the Emergency Department with:
- 1-day history of left-sided chest pain
- Pain was dull, worse with inspiration
- No clear relation to movement or position
- No associated symptoms
- Vital signs were completely normal
An ECG was performed.
What do you think of her ECG?
Key Findings
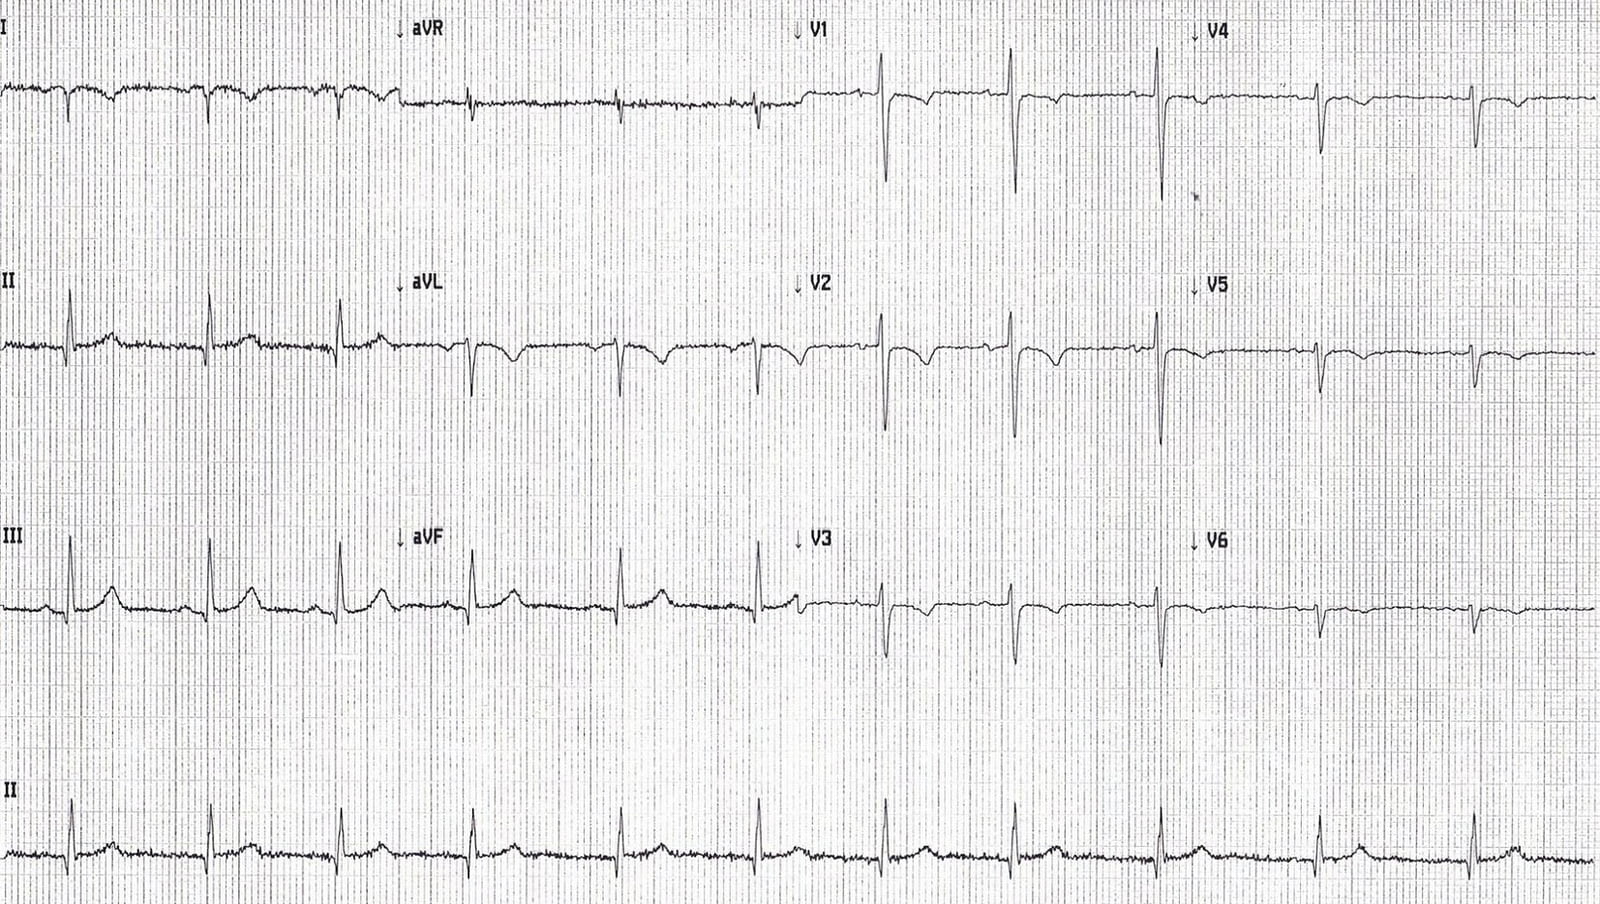
- P waves, QRS complexes, and T waves were negative in lead I and aVL.
- P wave was positive in aVR.
These features raise two important differentials:
- Limb Lead Malposition
- Dextrocardia
The ECG shown below demonstrated a pattern consistent with limb lead reversal — but is that the full story?
ECG Interpretation Clues
In limb lead malposition, chest leads remain normal because the issue is isolated to limb lead misplacement.
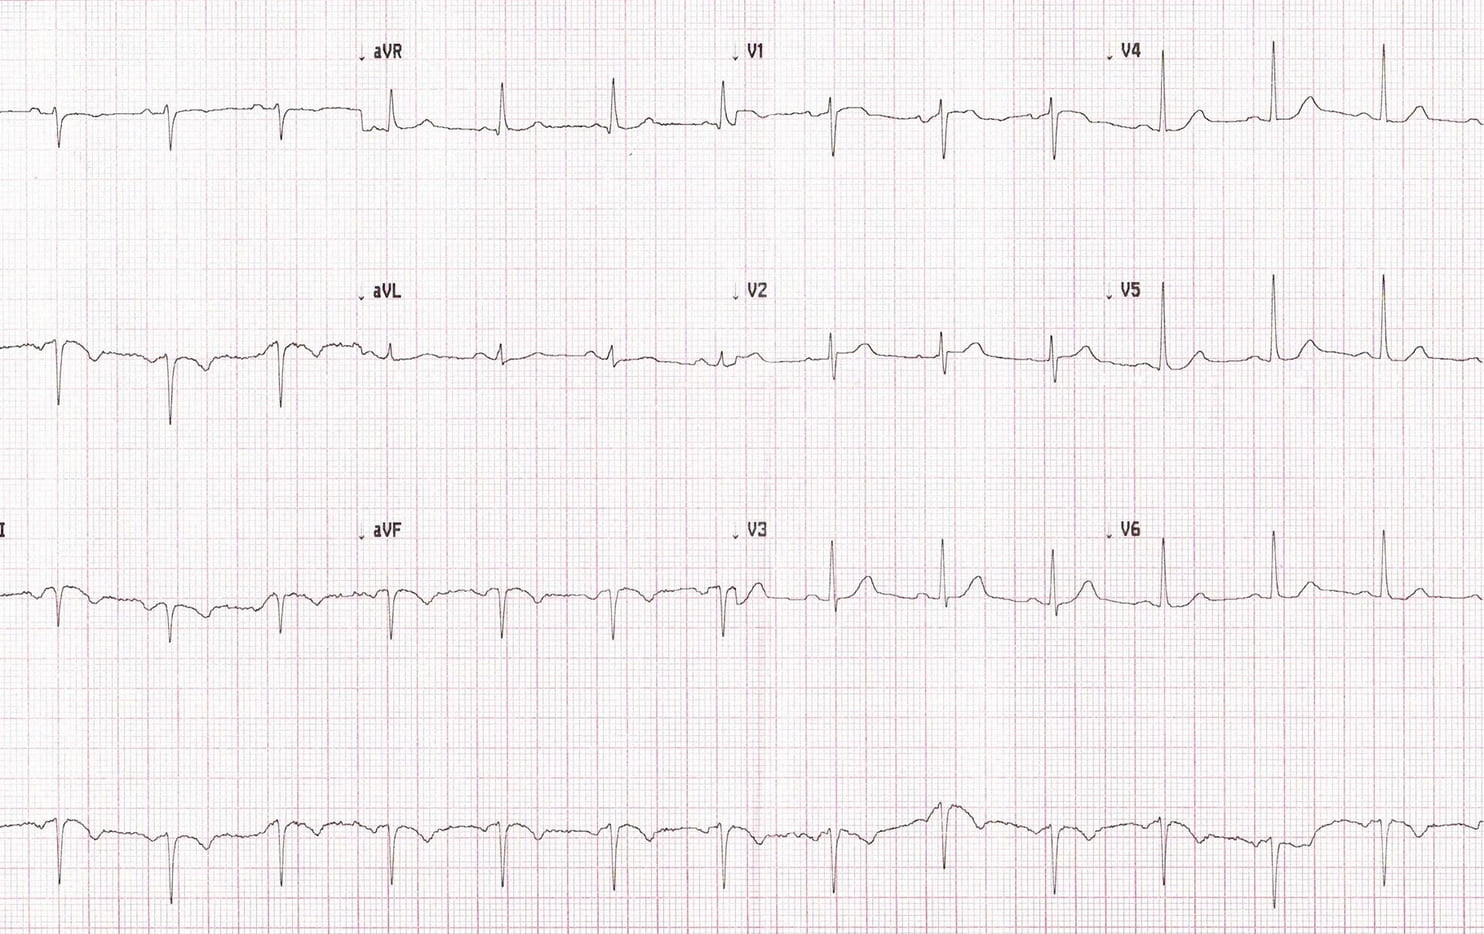
But in this case, there were additional abnormalities:
- Reversed R wave progression in chest leads (R wave starts tall in V1 and gets smaller toward V6)
- T wave inversion across the chest leads
- Progressively smaller QRS complexes from V1 to V6 — suggesting that the electrodes are moving away from the cardiac mass
Putting It All Together
When you combine:
- Limb lead reversal pattern
- Abnormal chest lead progression
- Inverted T waves in precordial leads
- Decreasing QRS amplitude across V1–V6
The most likely diagnosis is Dextrocardia.
Confirming the Diagnosis
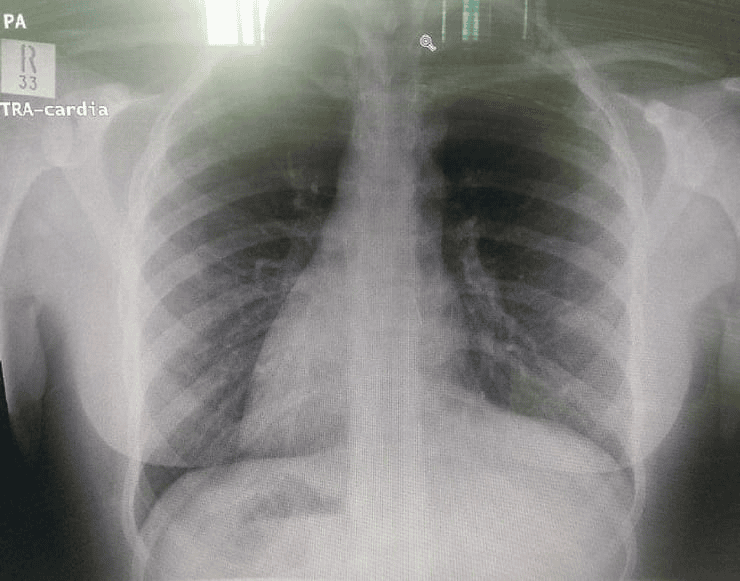
This patient had Dextrocardia with situs inversus totalis, confirmed by:
Chest X-ray Findings
- Gastric gas bubble on the right
- Liver shadow on the left
A right-sided ECG corrected the abnormalities in chest leads, confirming the heart is positioned in the right thorax.

Final Diagnosis and Disposition
- Patient had low pre-test probability for Pulmonary Embolism (PE).
- D-dimer was negative.
- She was discharged with the diagnosis of non-specific chest pain, likely costochondritis.
Further Learning
- Watch the full case discussion on YouTube
Key Takeaways
- Dextrocardia should be suspected when limb leads show reversed polarity and chest leads have reversed R wave progression.
- Limb lead malposition affects only limb leads; chest leads stay normal.
- A right-sided ECG is key to confirming true dextrocardia.
- Always consider anatomical variations in young patients with chest pain and unusual ECGs.
Frequently Asked Questions
How can you differentiate limb lead reversal from dextrocardia on ECG?
Limb lead reversal affects limb leads only, while dextrocardia also causes reversed R wave progression and abnormal chest lead patterns.
What are signs of dextrocardia on ECG?
Negative P/QRS/T waves in lead I and aVL, reversed R wave progression from V1–V6, and progressively smaller QRS complexes in precordial leads.
How is dextrocardia confirmed clinically?
With a chest X-ray showing situs inversus and/or a right-sided ECG that normalizes the waveforms.
Ready To Take Your Clinical Learning Further?
Explore structured ECG and emergency medicine courses built around practical clinical knowledge, real cases, and confident decision-making.