
Pericardial Effusion ECG Case: Low Voltage Misdiagnosed as Pulmonary Embolism “Small, Yet Dangerous”
Case Presentation (H2) A 52-year-old male with metastatic cancer undergoing chemotherapy presented to the Emergency Department with: Acute chest pain

Case Presentation
A 52-year-old male with metastatic cancer undergoing chemotherapy presented to the Emergency Department with:
- Acute chest pain
- Shortness of breath
Vital signs:
- Respiratory Rate: 26
- O₂ Saturation: 94% (on room air)
- Blood Pressure: 100/65 mmHg
- Heart Rate: 111 bpm
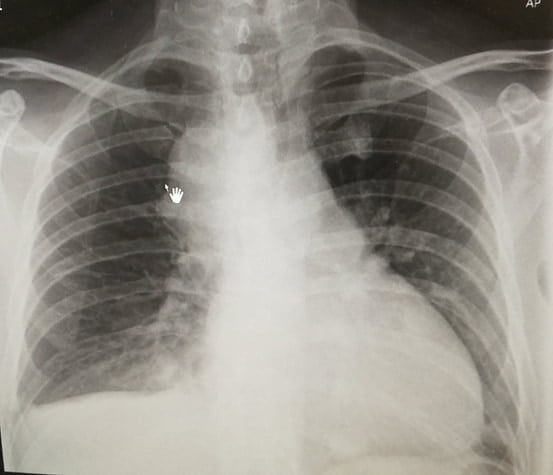
His chest X-ray (AP view) showed enlarged mediastinal lymph nodes, which were known.
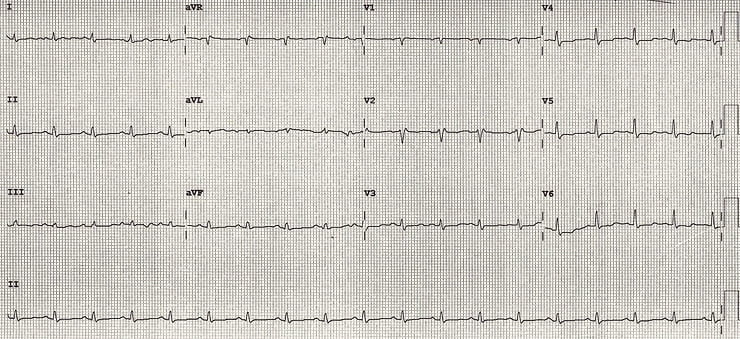
Then came the ECG — and the diagnosis.
What Is Your Diagnosis?
Let's walk through the case as it unfolded in real time.
First Impression: Suspected Pulmonary Embolism
The initial clinical picture strongly suggested PE:
- Active cancer
- Ongoing chemotherapy
- Sudden chest pain + SOB
- Tachypnea and tachycardia
He fit every box for anticoagulation and admission with planned CT Pulmonary Angiogram (CTPA).
But one key detail almost derailed everything…
Chest X-Ray Clue
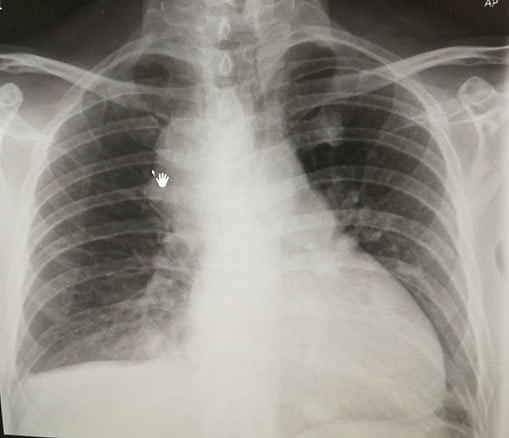
Although the CXR was AP view, cardiomegaly was evident.
This raised concern — and led to a closer look at the ECG.
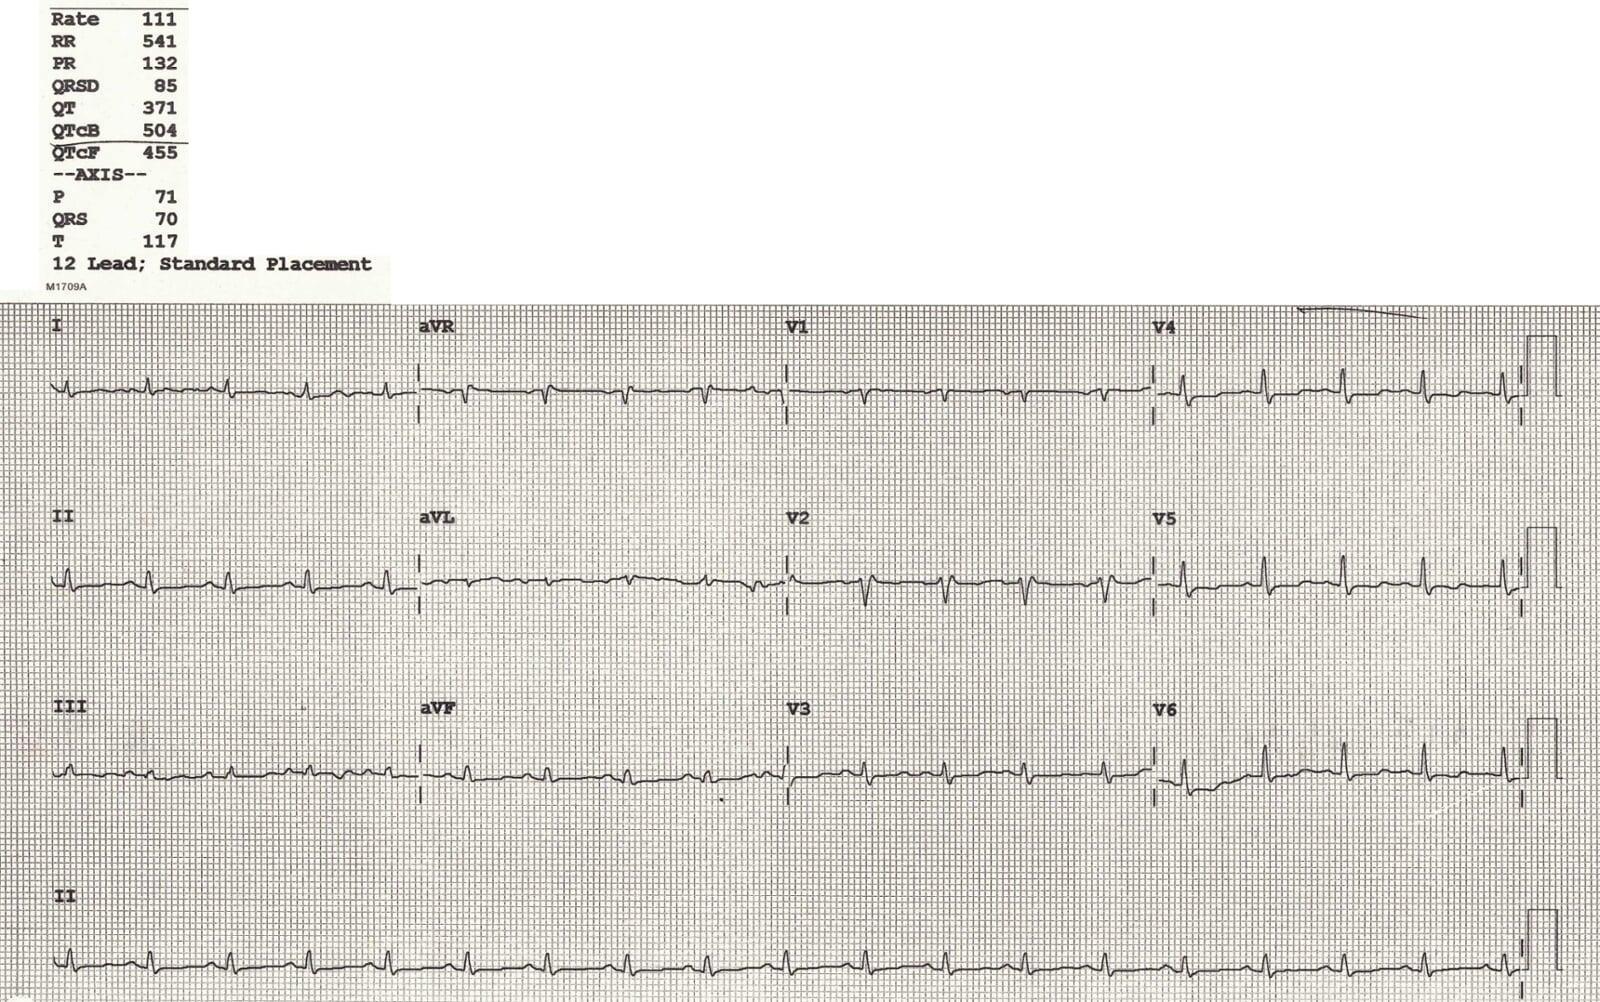
ECG Findings
The ECG showed two critical abnormalities:
- Prolonged QTc
- Low voltage ECG
About the Long QT
- Likely related to chemotherapy
- Electrolytes were not severely abnormal
- Covered in detail in a previous blog
Focus: Low Voltage ECG
Definition:
- Limb leads (I + II + III) total height < 15 small squares, and/or
- Precordial leads (V1–V3) total height < 30 small squares
Causes fall into two categories:
Poor Signal Generation by the Heart
- Cardiomyopathy
- Hypothyroidism
- Myocardial infiltration (e.g. sarcoidosis)
Barriers Between the Heart and Leads
- Fat (obesity)
- Air (COPD)
- Fluid (pericardial/pleural effusion)
Pattern Recognition: Tachycardia + Low Voltage
This combination strongly suggests:
Pericardial Effusion
Classic ECG Triad of Massive Pericardial Effusion
- Low Voltage ECG
- Tachycardia
- Electrical Alternans (not seen in this case)
Why This Matters
If this patient had been anticoagulated for presumed PE, he may have deteriorated due to hemorrhagic tamponade from undiagnosed pericardial effusion.
What Was Done
- Immediate bedside echo was performed → Confirmed pericardial effusion
- CTPA was expedited (to rule out PE before anticoagulating)
- CTPA showed no pulmonary embolism
Patient was safely admitted to CCU and did well.
Key Learning Points
- Low-voltage ECG is a powerful early clue.
- Tachycardia + Low Voltage = Think pericardial effusion.
- Don't treat presumed PE blindly — stop and confirm.
- CTPA + Echo combo is crucial when the diagnosis is unclear.
Further Learning
- LITFL ECG Library: Low Voltage Patterns
Frequently Asked Questions
What are the ECG criteria for diagnosing low voltage?
Limb leads I + II + III < 15 mm combined, or V1–V3 < 30 mm combined.
What are the most likely causes of low voltage with tachycardia?
Pericardial effusion is the most likely cause, especially in cancer patients or those with inflammatory conditions.
Why is anticoagulating blindly in suspected PE dangerous?
In cases like pericardial effusion, anticoagulation may lead to hemorrhagic tamponade and death.

Ready To Take Your Clinical Learning Further?
Explore structured ECG and emergency medicine courses built around practical clinical knowledge, real cases, and confident decision-making.